HIPAA News for Small and Mid-Sized Practices

Analysis of February 2018 Healthcare Data Breaches

Our February 2018 healthcare data breach report details the major data breaches reported by healthcare providers, health plans, and business associates in February 2018.

Summary of February 2018 Healthcare Data Breaches

February may have been a shorter month, but there was an increase in the number of healthcare data breaches reported to the Department of Health and Human Services’ Office for Civil Rights. In February, HIPAA covered entities and business associates reported 25 breaches – a 19% month on month increase in breaches.
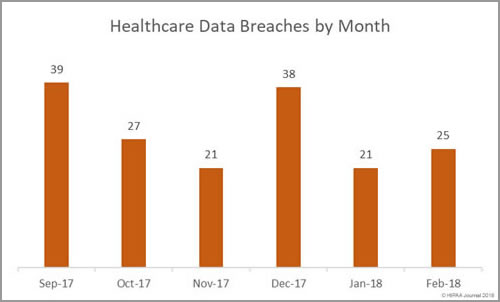
Healthcare Data Breaches by Month

While there was a higher breach tally this month, the number of healthcare records exposed as a result of healthcare data breaches fell by more than 100,000. In January 428,643 healthcare records were exposed. February 2018 healthcare data breaches saw 308,780 healthcare records exposed.
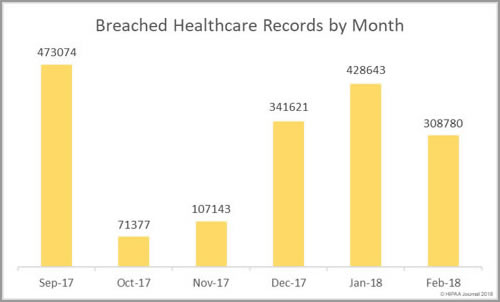
Records exposed in Healthcare Data Breaches

Largest Healthcare Data Breaches of February 2018

The largest healthcare data breaches reported to the Office for Civil Rights in February are listed below.

Covered Entity Covered Entity Type Individuals Affected Type of Breach Location of PHI
St. Peter’s Surgery & Endoscopy Center Healthcare Provider 134,512 Hacking/IT Incident Network Server
Tufts Associated Health Maintenance Organization, Inc. Health Plan 70,320 Unauthorized Access/Disclosure Paper/Films
Triple-S Advantage, Inc. Health Plan 36,305 Unauthorized Access/Disclosure Paper/Films
CarePlus Health Plan Health Plan 11,248 Unauthorized Access/Disclosure Paper/Films
Union Lake Supermarket, LLC Healthcare Provider 9,956 Improper Disposal Other Portable Electronic Device

The top five data breaches were responsible for 85% of all exposed healthcare records in February. The largest data breach – a malware-related incident at St. Peter’s Surgery & Endoscopy Center – accounted for 43.6% of the exposed healthcare records in February.

Main Causes of February 2018 Healthcare Data Breaches

Unauthorized access/disclosures topped the list of the main causes of healthcare data breaches in February 2018 with 12 incidents and included three of the most serious breaches. Hacking incidents were in close second with 9 breaches, followed by three loss/theft incidents and one case of improper disposal of ePHI.
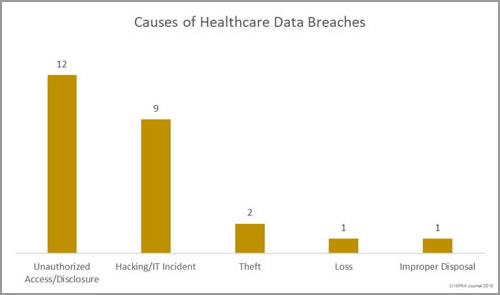
Causes of February 2018 Healthcare Data Breaches

Records Exposed by Breach Type

Hacking/IT incidents were the second biggest cause of healthcare data breaches in February, but the incidents resulted in the exposure/theft of the largest amount of healthcare data.
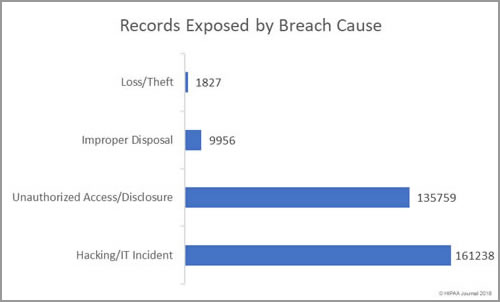
Records Exposed by Breach Type

Location of Breached Records

Overall, there were more breaches involving electronic health data than physical records, although breaches involving paper/films were the most numerous with 6 incidents. The breach reports show that while technological controls are essential to prevent hacks and unauthorized access/disclosures of electronic records, physical security is important for paper records and administrative safeguards are necessary to prevent unauthorized access. All six of the breaches involving paper/films were unauthorized access/disclosures.
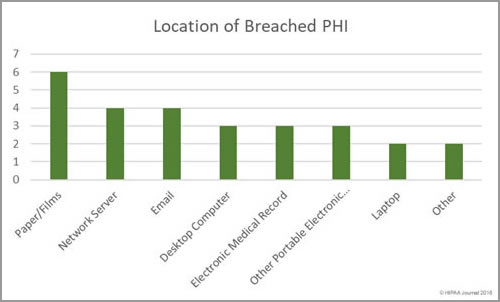
Location of breached healthcare records (February 2018)

Data Breaches by Covered Entity

Healthcare providers were the worst affected by data breaches in February with 15 incidents (reported by 14 healthcare providers). There were three breaches reported by pharmacies in February. 8 data breaches were reported by 7 health plans and two security incidents were reported by business associates.
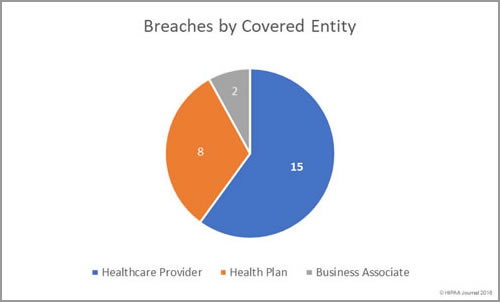
Data Breaches by Covered Entity (February 2018)

Healthcare provider breaches exposed the most health records in February. 168,732 records were exposed by healthcare providers. The mean breach size was 11,248 records and the median breach size was 1,670 records.

Health plans experienced fewer breaches, but the incidents were more severe. 133,580 records were exposed by health plans. The mean breach size was 16,698 records and the median breach size was 6,075 records. The mean and median breach size for business associate data breaches was 3,234 records.
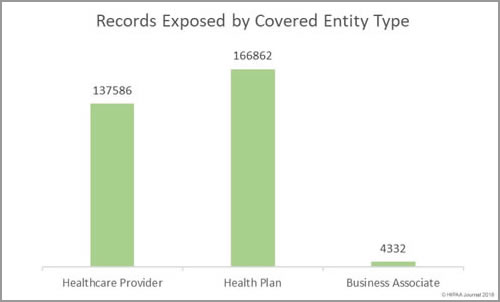
Records exposed by covered entity (February 2018)

February 2018 Healthcare Data Breaches by State

Healthcare organizations based in 18 states reported data breaches in February 2018. There were six states that experienced 2 data breaches– Alabama, California, Massachusetts, Mississippi, Rhode Island, and Wisconsin.

Arkansas, Connecticut, Illinois, Kentucky, Maine, Michigan, Missouri, North Carolina, New Jersey, New York, Tennessee, and Virginia each had one data breach reported.

Financial Penalties for HIPAA Covered Entities in February 2018

The Office for Civil Rights settled one HIPAA violation case in February. Filefax Inc, agreed to settle potential HIPAA violations with OCR for $100,000. The financial penalty sent a message to HIPAA-covered entities and their business associates that HIPAA responsibilities do not end when a business ceases trading. The fine relates to HIPAA violations that occurred after the business closed – the improper disposal of paperwork containing protected health information.

The post Analysis of February 2018 Healthcare Data Breaches appeared first on HIPAA Journal.

Survey Reveals 62% of Healthcare Organizations Have Experienced a Data Breach in the Past Year

A recent Ponemon Institute survey has revealed 62% of healthcare organizations have experienced a data breach in the past 12 months. More than half of those organizations experienced data loss as a result.

The Merlin International sponsored survey was conducted on 627 healthcare industry leaders from hospitals and payer organizations. 67% of respondents worked in hospitals with 100-500 beds and had an estimated 10,000 to 100,000 networked devices.

Last year more than 5 million healthcare records were exposed or stolen, and the healthcare was the second most targeted industry behind the business sector. 2017 was the fourth consecutive year that the healthcare industry has been second for data breaches and there are no signs that cyberattacks are likely to reduce over the coming year.

Even though there is a high probability of experiencing a cyberattack, 51% of surveyed organizations have yet to implement an incident response program. This lack of preparedness can hamper recovery if a cyberattack is experienced. As the Cost of a Data Breach Study by the Ponemon Institute showed, a fast response to a data breach can limit the harm caused to breach victims and reduce the cost of mitigating such an attack. Respondents reported that the cost of mitigating an attack and dealing with the fallout from a network compromise was approximately $4 million.

When asked about the biggest threats to their organization and the types of attack that caused the most concern there was little to choose between internal and external threats, which were rated as a top concern by 64% and 63% of respondents respectively. The main perceived targets for hackers were electronic medical records (77%), patient billing information (56%), login credentials (54%), other authentication credentials (49%), and research information (45%).

The methods used to gain access to networks and data were highly varied. The main method of attack was the exploitation of software and operating system vulnerabilities and the use of malware. 71% of respondents said vulnerabilities were exploited while 69% said attacks involved the use of malware. 37% of organizations had experienced ransomware attacks.

The security of medical devices is a major concern, especially since they are a blind spot in many organizations. 65% of respondents said medical devices were not included in their overall cybersecurity strategy or they didn’t know if they were. 31% of respondents said they did not have any plans to include medical devices in their cybersecurity strategies in the near future.

The HHS’ Office for Civil Rights has raised awareness of the need to provide ongoing security awareness training to staff and companies such as Cofense have published data to show how security awareness training and phishing simulations can greatly reduce susceptibility to phishing attacks. However, many healthcare organizations are not heeding that advice and are not providing training regularly. Many healthcare organizations are still only providing security awareness training to employees annually. It is therefore unsurprising that 52% of respondents said a lack of employee security awareness was hampering their ability to improve their security posture.

74% believed the biggest obstacle preventing them from improving security was staffing issues and 60% said they do not have staff with the right cybersecurity qualifications in-house. 51% of respondents said that have not yet appointed a Chief Information Security Officer (CISO).

The post Survey Reveals 62% of Healthcare Organizations Have Experienced a Data Breach in the Past Year appeared first on HIPAA Journal.

Is it a HIPAA Violation to Email Patient Names?

We have been asked is it a HIPAA violation to email patient names and other protected health information? In answer to this and similar questions, we will clarify how HIPAA relates to email and explain some of the precautions HIPAA covered entities and healthcare employees should take to ensure compliance when using email to send electronic protected health information.

Is it a HIPAA Violation to Email Patient Names?

Patient names (first and last name or last name and initial) are one of the 18 identifiers classed as protected health information (PHI) in the HIPAA Privacy Rule.

HIPAA does not prohibit the electronic transmission of PHI. Electronic communications, including email, are permitted, although HIPAA-covered entities must apply reasonable safeguards when transmitting ePHI to ensure the confidentiality and integrity of data.

It is not a HIPAA violation to email patient names per se, although patient names and other PHI should not be included in the subject lines of emails as the information could easily be viewed by unauthorized individuals. Even when messages are protected with encryption in transit, message headers – which include the subject line and to and from fields – are often not encrypted and could potentially be intercepted and viewed.

Patients names and other PHI should only be sent to individuals authorized to receive that information, so care must be taken to ensure the email is addressed correctly. Sending an email containing PHI to an incorrect recipient would be an unauthorized disclosure and a violation of HIPAA.

Must all Emails Containing PHI be Encrypted?

HIPAA does not require the use of encryption. Encryption is only an addressable standard. However, if, following a risk assessment, the decision is taken not to use encryption, an alternative and equivalent security measure must be used in its place.

In the case of internal emails, it would not be necessary for messages containing ePHI to be encrypted provided the messages are only sent via an internal email system and do not leave the protection of a firewall. Access controls would also need to be in place to prevent messages from being opened by individuals not authorized to receive the information.

If emails containing PHI are sent outside the protection of an internal network there is considerable potential for PHI to be viewed by unauthorized individuals. This is not a problem when emailing patients, provided consent to use email to send PHI has been obtained from the patient in advance. The patient must have been made aware of the risks of sending PHI via unencrypted email and must have given authorization to use such a potentially insecure method of communication.

Emailing ePHI to all other individuals using unencrypted email is a risky strategy. While HIPAA encryption requirements are somewhat vague, in the event of a HIPAA audit or data breach investigation, it would be hard to argue that ePHI sent via unencrypted mail was reasonably protected, especially when there are many secure methods of data sharing available – Dropbox, Google Drive, Box etc.

The post Is it a HIPAA Violation to Email Patient Names? appeared first on HIPAA Journal.

2018 HIPAA Changes and Enforcement Outlook

Are there likely to be major 2018 HIPAA changes? What does this year have in store in terms of new HIPAA regulations? OCR Director Roger Severino has hinted there could be some 2018 HIPAA changes and that HIPAA enforcement in 2018 is unlikely to slowdown.

Are Major 2018 HIPAA Changes Likely?

The Trump administration has made it clear that there should be a decrease rather than an increase in regulation in the United States. In January 2017, Trump signed an executive order calling for a reduction in regulation, which was seen to be hampering America’s economic growth. At the time Trump said, “If there’s a new regulation, they have to knock out two. But it goes far beyond that, we’re cutting regulations massively for small business and for large business.”

While Trump was not specifically referring to healthcare, it is clear we are currently in a period of deregulation. Trump’s words were recently echoed by Severino at the HIMSS conference who confirmed the HSS understands deregulation in some areas is required before further regulations can be introduced.

Therefore, there are unlikely to be major 2018 HIPAA changes, at lease not in terms of increased regulation. What is more likely is an easing of the administrative burden on healthcare organizations in 2018.

OCR is currently reviewing existing HIPAA regulations to determine whether all aspects of HIPAA Rules are still relevant and if there are any areas where the administrative burden on healthcare organizations can be eased. OCR is looking at the benefit of various provisions of HIPAA and whether those benefits outweigh the costs.

The HHS has said its goals are “reducing the burden of compliance” and “streamlining its regulations,” while promoting “meaningful information sharing”.

2018 HIPAA changes could make life simpler for many healthcare organizations as the HHS attempts to minimize duplication and burdensome requirements and eliminate outdated restrictions and obsolete regulations.

HIPAA Enforcement in 2018

In 2016 there was a significant increase in HIPAA enforcement activities by OCR with more settlements reached with covered entities and business associates than any other year since the HIPAA Enforcement Rule was signed into law. In 2016 there were 12 settlements and one civil monetary penalty issued and 2017 HIPAA settlements were well above average levels, with 9 settlements and one civil monetary penalty. So, what can we expect for HIPAA enforcement in 2018?

At HIMSS 2018, Roger Severino gave a presentation on HIPAA compliance, enforcement, and policy updates from the Office for Civil Rights and made it clear OCR will continue to pursue settlements with HIPAA covered entities for egregious violations of HIPAA Rules. Severino said OCR still has the same enforcement mindset and that there will be “no slowdown in our enforcement efforts,” and “we’re still looking for big, juicy, egregious cases.” That does not necessarily mean large healthcare organizations. OCR treats potential HIPAA violations on a case by case basis, and smaller healthcare organizations may similarly be punished if they are discovered to have violated HIPAA Rules.

Severino said OCR does not want to fine healthcare organizations for violating HIPAA Rules and wants the settlements to reduce, but for that to happen, healthcare organizations must improve their compliance programs. 2018 HIPAA enforcement is likely to continue to see financial penalties issued for common HIPAA violations such as the failure to conduct regular risk assessments.  Already, 2018 has seen two settlements announced. A $100,000 penalty for Filefax, Inc., and a $3,500,000 settlement with Fresenius Medical Care North America. Time will tell if this was a blip or if that pace will be maintained throughout the year.

OCR is not the only enforcer of HIPAA Rules. State attorneys general can also issue fines for HIPAA violations, and the New York AG has been active in this area in recent weeks, fining EmblemHealth $575,000 in March and Aetna $1,150,000 in January. Further financial settlements are likely to be pursued in NY and other states to resolve HIPAA violations and privacy and security-related breaches of state laws.

The post 2018 HIPAA Changes and Enforcement Outlook appeared first on HIPAA Journal.

Is Office 365 HIPAA Compliant?

Is Microsoft Office 365 HIPAA compliant? Can healthcare organizations use Office 365 and remain in compliance with HIPAA and HITECH Act Rules?

What is Office 365?

Office 365 is a suite of subscription products developed by Microsoft that includes Word, Excel, PowerPoint, OneNote, Outlook, Publisher, and Access.

Office 365 for Healthcare

Microsoft is willing to enter into a business associate agreement (BAA) with HIPAA covered entities for Office 365 and Microsoft Dynamics CRM Online, provided the latter is purchased through Volume Licensing Programs or the Dynamics CRM Online Portal. The Microsoft BAA also covers the use of the Microsoft Azure cloud platform.

Microsoft does not demand that a BAA be obtained prior to use of Office 365, as the BAA is automatically made available to customers with an online service contract. However, HIPAA covered entities should obtain a BAA prior to use of Office 365 in conjunction with any electronic protected health information (ePHI). They should also specify an administrative contact. In the event of a security breach, the administrative contact will be notified of a breach by Microsoft.

While there are companies that offer HIPAA certification to confirm that a company or product complies with HIPAA Rules, there is no official certification recognized by the HHS’ Office for Civil Rights or other federal agencies. However, Microsoft has undergone independent audits under ISO 27001 which incorporate assessments of security practices recommended by the HHS. Office 365 has been verified as having all necessary privacy and security controls to comply with HIPAA Rules.

Office 365 Security

All data uploaded to or stored on Microsoft servers is protected by encryption and any data transferred outside of Microsoft facilities is similarly encrypted.  However, packet headers and message headers are not encrypted.

Provided ePHI is not entered into the subject line of emails, the names of files attached to emails, or is used in the to and from fields of emails, email can be used securely.

Microsoft Office 365 meets HIPAA auditing requirements and logs of access to stored data are maintained. Reports on access logs can be obtained from Microsoft on request.

Microsoft offers 2-factor authentication to prevent Office 365 and Outlook email accounts from being accessed if a password is compromised and an unfamiliar device attempts to log into an account.

Is Microsoft Office 365 HIPAA Compliant?

So, is Microsoft Office 365 HIPAA compliant? Provided a HIPAA-covered entity has entered into a business associate agreement with Microsoft, Office 365 can be used in a manner compliant with HIPAA Rules.

While all appropriate privacy and security controls have been implemented by Microsoft to ensure that Office 365 can be used by HIPAA-covered entities while remaining compliant with HIPAA and the HITECH Act, use of Office 365 does not guarantee compliance, even if a BAA has been obtained from Microsoft.

It is the responsibility of covered entities to ensure access controls are configured correctly, administrator access tracking is turned on, Microsoft Dynamics CRM Online for supported devices is turned off, access control reports are obtained and checked regularly, and all users are trained how to use Office 365 in a manner compliant with HIPAA Rules.

The post Is Office 365 HIPAA Compliant? appeared first on HIPAA Journal.

Alabama Data Breach Notification Act Passed by State Senate

The Alabama Data Breach Notification Act (Senate Bill 318) has advanced for consideration by the House of Representatives after being unanimously passed by the Alabama Senate last week.

Alabama is one of two states that has yet to introduce legislation that requires companies to issue notifications to individuals whose personal information is exposed in data breaches. The other state – South Dakota – is also considering introducing similar legislation to protect state residents.

The Alabama Data Breach Notification Act, proposed by Sen. Arthur Orr (R-Decatur), requires companies doing business in the state of Alabama to issue notifications to state residents when their sensitive personal information has been exposed and it is reasonably likely to result in breach victims coming to substantial harm.

Entities that would be required to comply with the Alabama Data Breach Notification Act are persons,

sole proprietorships, partnerships, government entities, corporations, non-profits, trusts, estates, cooperative associations, and other business entities that acquire or use sensitive personally identifying information.

Sensitive personally identifying information is defined as a first name/first initial and last name combined with any of the following data elements, provided they are not truncated, encrypted, or hashed:

  • Social Security number
  • Tax ID number
  • Driver’s license number
  • State identification card number
  • Military identification number
  • Passport number
  • Other unique government identification number
  • Medical information such as health history, treatment or diagnosis or mental/physical condition
  • Health insurance number or unique identifiers used by health insurers for identification of an individual
  • Financial account number (bank account, credit card, or debit card) combined with an expiry date, security code, PIN, password, or other information that would allow a financial transaction to be conducted
  • Username or email address along with a password or security question answer that would allow an account to be accessed

The Alabama Data Breach Notification Act also calls for entities holding the above information to implement and maintain reasonable security measures to protect sensitive personally identifiable information. A risk analysis must be conducted to identity potential security risks and safeguards would need to be adopted reduce those risks to a reasonable level. Measures to protect data should be appropriate for the sensitivity of the data, the amount of data held, the size of the organization, and the cost of safeguards relative to the company’s resources.

If the Alabama Data Breach Notification Act is passed, state residents would have to be notified of data breaches within 45 days of discovery of a breach. Companies that fail to issue the notifications could potentially be fined up to $5,000 per day for any delay in issuing notifications up to a maximum of $500,000 per breach. Lawsuits could be filed by the attorney general’s office on behalf of breach victims, although private actions would not be possible.

Breach notices would be required to include the date or estimated date of the breach, a description of the information exposed, details of the steps that can be taken by breach victims to protect themselves against harm, details of the steps taken by the breached entity to restore security and confidentiality of data, and contact information for further information about the breach. A breach notice would also need to be submitted to the state attorney general’s office if the breach impacts more than 1,000 individuals.

In contrast to data breach notification laws in some US states that exempt HIPAA covered entities that are in compliance with HIPAA laws, the Alabama Data Breach Notification Act would apply to HIPAA covered entities.

The current maximum time frame for HIPAA covered entities is 60 days from the date of discovery of a breach. For Alabama residents at least, that time frame would be reduced by 15 days.

The post Alabama Data Breach Notification Act Passed by State Senate appeared first on HIPAA Journal.

Is a HIPAA Violation Grounds for Termination?

Is a HIPAA violation grounds for termination? What actions are healthcare organizations likely to take if they discover an employee has violated HIPAA Rules?

Since the introduction of the HIPAA Enforcement Rule, the HHS’ Office for Civil Rights has been able to pursue financial penalties for HIPAA violations. Organizations discovered to have violated HIPAA Rules or failed to have implemented policies and procedures in line with HIPAA Rules can face severe financial penalties. But what about individual employees who accidentally or deliberately violate HIPAA and patient privacy?

Do Most Healthcare Organizations Consider a HIPAA Violation Grounds for Termination?

Not all HIPAA violations are equal, although any violation of HIPAA Rules is a serious matter that warrants investigation and action by healthcare organizations.

When a HIPAA violation is reported – by an employee, colleague or patient – healthcare organizations will investigate the incident and will attempt to determine whether HIPAA laws were violated, and if so, how the violation occurred, the implications for patients whose privacy has been violated, potential legal issues arising from the violation and possible action by regulators. Healthcare organizations will be keen to take action to ensure that similar violations are prevented in the future.

When an employee is discovered to have knowingly or unknowingly violated HIPAA Rules there are likely to be repercussions for the individual concerned.

An unintentional acquisition, access, or use of protected health information by a workforce member in which the acquisition, access, or use was made in good faith and within the scope of authority would not be a reportable breach and may not necessarily result in disciplinary action.

Some healthcare organizations have strict rules on violations of HIPAA Rules and regularly terminate employees for HIPAA violations. Others have a policy of dealing with minor HIPAA violations internally. Depending on the nature of the violation, the incident may warrant disciplinary action against the individual concerned which could see the employee suspended pending an investigation. Termination for a HIPAA violation is a possible outcome.

Ultimately the repercussions for a HIPAA violation will depend on the polices in place at an organization and the severity of the violation. A violation of the Minimum Necessary Information Standard may, depending on the circumstances, be considered a matter for internal disciplinary action and not termination. Viewing the medical records of any patient without authorization is likely to result in termination unless the incident is reported quickly, no harm was caused to the patient, and access was accidental or made in good faith.

Recent Cases Where Healthcare Providers Deemed a HIPAA Violation Grounds for Termination

Criminal Penalties for HIPAA Violations

Termination may not be the worst that can happen when HIPAA Rules are violated by employees. Healthcare employees may be found criminally liable for HIPAA violations and cases can be referred to the Department of Justice for prosecution.

Criminal violations of HIPAA Rules can result in financial penalties and jail time for healthcare employees. A fine of up to $50,000 and one year in jail is possible when PHI is knowingly obtained and impermissibly disclosed. A fine of up to $100,000 and five years in jail is possible for violations involving false pretenses, and a fine of up to $250,000 and up to 10 years in jail is possible when HIPAA Rules have been violated for malicious reasons or for personal gain. A further 2 years can be added onto the sentence for aggravated identity theft.

The post Is a HIPAA Violation Grounds for Termination? appeared first on HIPAA Journal.

EmblemHealth Fined $575,000 by NY Attorney General for HIPAA Breach

A 2016 mailing error by EmblemHealth that saw the Health Insurance Claim Numbers of 81,122 plan members printed on the outside of envelopes has resulted in a $575,000 settlement with the New York Attorney General.

While all mailings include a unique patient identifier on the envelope, in this case the potential for harm was considerable as Health Insurance Claim numbers are formed using the Social Security numbers of plan members.

Announcing the settlement, New York Attorney General Eric T. Schneiderman explained that Health Insurance Portability and Accountability Act (HIPAA) Rules require HIPAA covered entities to implement administrative, physical, and technical safeguards to ensure the confidentiality of patients’ and plan members’ protected health information.

The error that saw Social Security numbers exposed violated HIPAA Rules. EmblemHealth failed to comply with “many standards and procedural specifications” required by HIPAA. Attorney General Schneiderman also said that printing Social Security numbers on the outside of envelopes violated New York General Business Law § 399-ddd(2)(e).

In addition to the $575,000 settlement, EmblemHealth is required to adopt a robust corrective action plan that requires a comprehensive risk analysis to be conducted related to the mailing of policy documents. The results of that risk analysis must be reported to the Attorney General’s office within 180 days. Policies and procedures related to mailings must also be reviewed and updated based on the findings of the risk analysis.

EmblemHealth must catalogue, review, and monitor mailings and ensure that all employees involved in mailings receive appropriate training. They must also be instructed to report any violations of the HIPAA Minimum Necessary Standard to EmblemHealth officials to allow prompt action to be taken manage risks to plan members. EmblemHealth is also required to report all security incidents to the Attorney General’s office for a period of 3 years from the date of the settlement.

According to Attorney General Schneiderman, New York has “weak and outdated security laws” which he has attempted to address by introducing the ‘Stop Hacks and Improve Electronic Data Security (SHIELD) Act’ in November 2017. There will now be a further push to get the SHIELD Act passed. Schneiderman claims the SHIELD Act will improve protections for state residents. Businesses will also be held accountable for data breaches that result in customers’ personal data being exposed.

“The careless handling of social security numbers is never acceptable,” said Attorney General Schneiderman. “New Yorkers need to be able to trust that companies entrusted with their private information will guard it appropriately. This starts with good governance—which is why my office will continue to push for stronger security laws and hold businesses accountable for protecting their customers’ personal data.”

The post EmblemHealth Fined $575,000 by NY Attorney General for HIPAA Breach appeared first on HIPAA Journal.

Is Google Slides HIPAA Compliant?

Is Google Slides HIPAA compliant? Can Google Slides be used by healthcare organizations without violating HIPAA Rules? This post explores whether Google Slides is HIPAA compliant and whether it is possible to use the presentation editor in connection with electronic protected health information.

Google Slides is a presentation editor that allows users to create slide shows, training material, and project presentations. It is an ideal option for users who do not regularly create slide shows or presentations and do not have a software package that offers the same functionality. Google Slides is available free of charge for consumers to use and is equivalent to Microsoft’s PowerPoint.

Healthcare organizations that are looking to create training courses and slideshows that involve the use of data protected by HIPAA need to exercise caution. Use of Google Slides with electronic protected health information could potentially violate HIPAA Rules and patient privacy. That could all too easily result in a financial penalty.

Google Slides is a web-based presentation program that is not exempt from HIPAA under the HIPAA Conduit Exception Rule. The use of any ePHI with Google Slides is prohibited by the Privacy Rule unless healthcare organizations enter into a business associate agreement with Google prior to the use of Google Slides.

How to Make Google Slides HIPAA Compliant

The first step to take before using Google Slides in connection with any ePHI is to enter into a business associate agreement with Google. Google offers a BAA for healthcare organizations covering G Suite and Google Drive, which includes Google Docs, Google Sheets, Google Forms, and Google Slides.

As with all Google Drive services, it is essential to control who has access to files created on Google Drive. Healthcare organizations must ensure that any files created can only be accessed by individuals authorized to view the files and links to the files can only be shared with specific people. Sharing permissions should be carefully configured to prevent any accidental disclosures of ePHI.

It is important that no ePHI is included in the titles of any files created on Google Drive and third-party applications should be disabled. If applications need to be used, the security of those applications must be assessed and the developer’s documentation carefully checked. Third-party application developers would also be considered business associates and BAAs would be necessary.

Provided a BAA has been obtained from Google, Google Drive permissions are configured correctly, and best practices are followed, the Google Drive suite of products can be used by healthcare organizations in connection with ePHI.

The post Is Google Slides HIPAA Compliant? appeared first on HIPAA Journal.