Healthcare Data Privacy

Colorado Considers New Privacy and Data Breach Legislation

Colorado is the latest state to consider changing its privacy and data breach notification laws to improve protections for state residents. The legislation has been proposed by a bipartisan group of legislators, and if passed, would make considerable changes to existing state laws.

The proposed legislation applies to personally identifying information. The changes would see the following information included in the definition of PII:

Full name or last name and initial in combination with any of the following data elements: Personal ID numbers, Social Security numbers, state ID numbers, state or government driver’s license numbers, passport numbers, biometric data, passwords and pass codes, employment, student and military IDs, financial transaction devices, health information, and health insurance information.

Usernames/email addresses, financial account numbers, and credit/debit card numbers are also included, if they are compromised along with other information that allows account access or use. A breach would not be deemed to have occurred if the PII is encrypted, unless the key to unlock the encryption is also compromised.

Organizations that store the PII of state residents would be required to implement controls to ensure the privacy and confidentiality of PII. The proposed legislation does not include details of the types of security protections, procedures, and practices that must be implemented to keep personally identifiable information secure, only that the security measures be “appropriate to the nature of the personally identifying information and the nature and size of the business and its operations.”

Any entity that wishes to disclose PII to a third party must communicate to that entity that the PII must be protected and secured at all times, including the use of technology, procedures and practices. They must be appropriate to the sensitivity of the data and be reasonably designed to help protect the PII from unauthorized access, use, modification, disclosure, or destruction.

If PII is no longer required, the information must be securely and permanently destroyed, whether the information is in paper form or stored on electronic devices. Policies covering the destruction of data are required in writing.

For paper records, this would likely mean burning, pulping, pulverizing, or shredding. For electric devices, data would need to be securely erased to prevent reconstruction. Typical methods include degaussing – the exposure of the device to strong magnetic fields, the use of software to overwrite media to prevent reconstruction of data, or destroying the media by pulverization, disintegration, melting, shredding, or incineration.

In the event of a breach of PII, the maximum time limit for issuing notifications would be 45 days from the discovery of a breach. Currently there is no stipulated maximum time frame for issuing notifications. Notifications must currently be issued “in the most expedient time and without unreasonable delay.”

A notification would also need to be sent to the state attorney general no later than 7 days following the discovery of a breach that impacts 500 or more individuals.

As is the case in California and several other states, the legislation stipulates the content that must be included in the breach notification letters.  The date of the breach must be communicated, or a reasonable estimate if it is not known, a description of the PII that has been compromised, contact information, a toll-free number to call for further information, contact details of consumer reporting agencies and the FTC, and information on how credit freezes and security alerts can be set.

The legislation would also authorize the Colorado Attorney General to initiate criminal investigations and legal proceedings against organizations that fail to comply with the legislation

The post Colorado Considers New Privacy and Data Breach Legislation appeared first on HIPAA Journal.

Analysis of Q4 2017 Healthcare Security Breaches

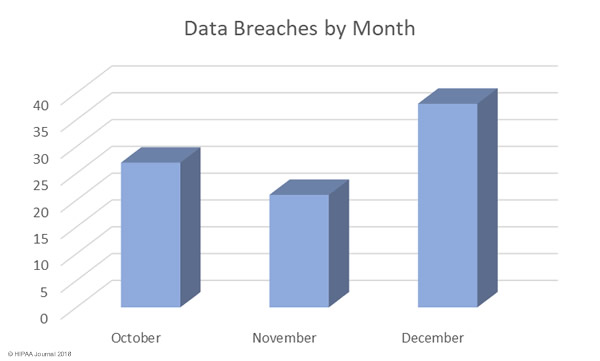
Q4, 2017 saw a 13% reduction in healthcare security breaches reported to the Department of Health and Human Services’ Office for Civil Rights. There were 99 data breaches reported in Q3, 2017. In Q4, there were 86 security breaches reported.

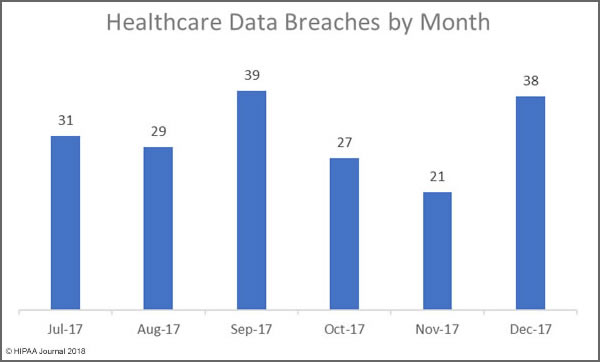
There were 27 healthcare security breaches reported in September, following by a major decline in breaches in November, when 21 incidents were reported. However, December saw a significant uptick in incidents with 38 reported breaches.

Q4 2017 Healthcare Security Breaches by Month

Accompanied by the quarterly decline in security incidents was a marked decrease in the severity of breaches. In Q3, there were 8 data breaches reported that impacted more than 50,000 individuals. In Q4, no breaches on that scale were reported. The largest incident in Q4 impacted 47,000 individuals.

 Largest Q4, 2017 Healthcare Security Breaches


Covered Entity Entity Type Number of Records Breached Cause of Breach
Oklahoma Department of Human Services Health Plan 47000 Hacking/IT Incident
Henry Ford Health System Healthcare Provider 43563 Theft
Coplin Health Systems Healthcare Provider 43000 Theft
Pulmonary Specialists of Louisville, PSC Healthcare Provider 32000 Hacking/IT Incident
SSM Health Healthcare Provider 29579 Unauthorized Access/Disclosure
UNC Health Care System Healthcare Provider 27113 Theft
Emory Healthcare Healthcare Provider 24000 Unauthorized Access/Disclosure
Franciscan Physician Network of Illinois and Specialty Physicians of Illinois, LLC (formerly known as WellGroup Health Partners, LLC) Healthcare Provider 22000 Loss
Chase Brexton Health Care Healthcare Provider 16562 Hacking/IT Incident
Hackensack Sleep and Pulmonary Center Healthcare Provider 16474 Hacking/IT Incident
Longs Peak Family Practice, P.C. Healthcare Provider 16238 Hacking/IT Incident
Shop-Rite Supermarkets, Incorporated Healthcare Provider 12172 Improper Disposal
Sinai Health System Healthcare Provider 11347 Hacking/IT Incident
The Medical College of Wisconsin, Inc. Healthcare Provider 9500 Hacking/IT Incident
Golden Rule Insurance Company Health Plan 9305 Unauthorized Access/Disclosure


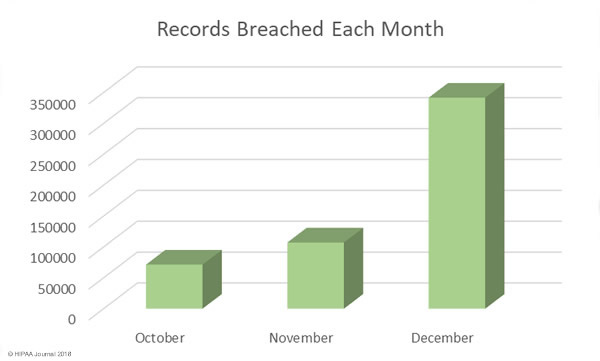
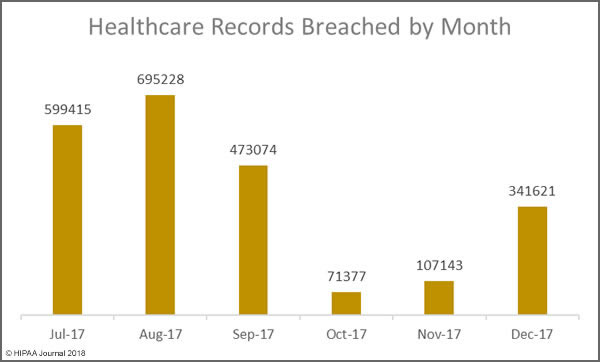
There was a steady increase in breached records each month in Q4. In October, 71,377 records were breached, rising to 107,143 records in November and 341,621 records in December. Even December’s high total was lower than any month in the previous quarter.

Q4 2017 Healthcare Security Breaches - breached records


Hacking/IT incidents tend to involve the highest number of exposed/stolen records and Q4 was no exception. 7 of the top 15 security incidents (47%) were due to hacks and IT incidents. Loss and theft incidents accounted for 27% of the worst healthcare security breaches in Q4, followed by unauthorized access/disclosures on 20%.

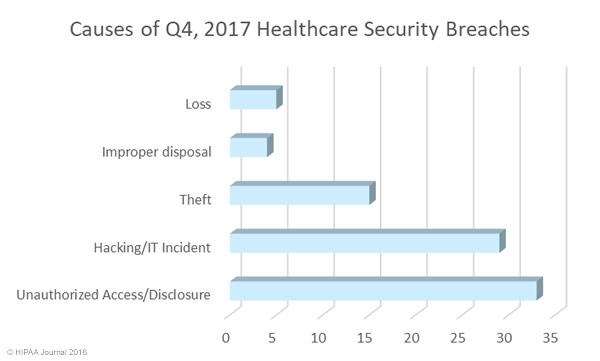
Causes of Q4 2017 Healthcare Security Breaches


While hacking/IT incidents resulted in the exposure/theft of the most records, unauthorized access/disclosure incidents were the most numerous. Out of the 86 reported healthcare security breaches in Q4, 33 were unauthorized access/disclosures (38.37%). There were 29 hacking/IT incidents (33.7%), and 20 incidents (23.3%) involving the loss/theft of PHI and electronic devices containing ePHI. Four incidents (4.7%) involved the improper disposal of PHI/ePHI.

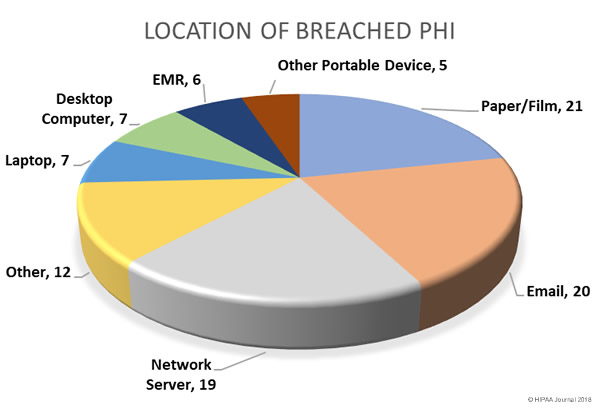
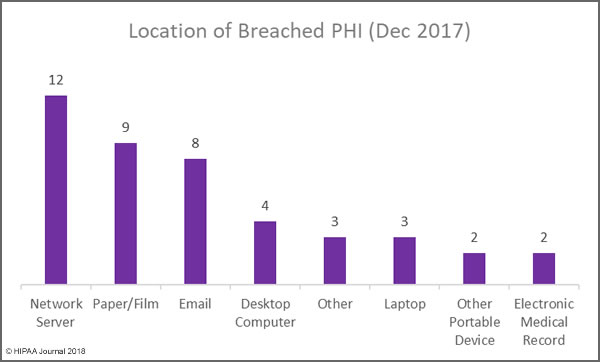
In Q4, paper records/films were involved in the most breaches, showing how important it is to physically secure records. 21 incidents (24.4%) involved physical records. As was the case in Q3, email was also a top three cause of breaches, with many healthcare organizations suffering phishing attacks in Q4. Network server attacks completed the top three locations of breached PHI.

Q4 2017 Healthcare Security Breaches - location of breached PHI


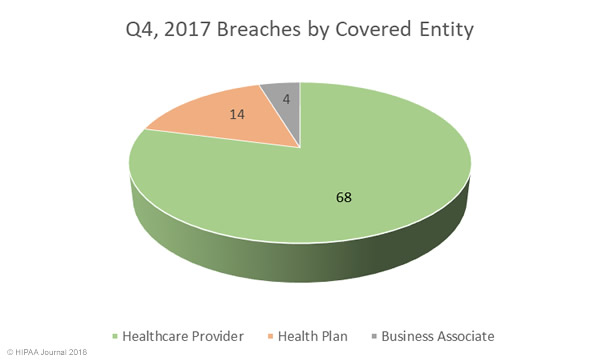
Healthcare providers reported the most security breaches in Q4, following by health plans and business associates of HIPAA-covered entities, as was the case for most of 2017.

Q4 2017 Healthcare Security Breaches by covered entity


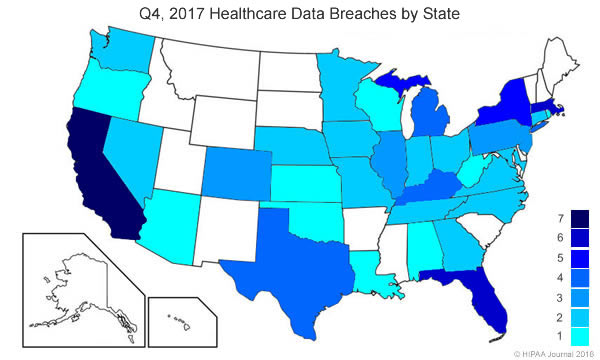
In Q4, 2017, healthcare organizations based in 35 states reported security breaches. Unsurprisingly, being the most populous state in the US, California topped the list for the most reported healthcare security breaches with 7 incidents in Q4.

In close second on 6 breaches were Florida and Maryland, followed by New York with 5 incidents. Kentucky, Michigan, and Texas each had four reported breaches, and Colorado, Illinois, New Jersey, and Pennsylvania each suffered 3 incidents.

Q4 2017 Healthcare Security Breaches - by state


The post Analysis of Q4 2017 Healthcare Security Breaches appeared first on HIPAA Journal.
HIPAA Covered Entities Urged to Address Spectre and Meltdown Chip Vulnerabilities

The Office for Civil Rights has sent an email update on the Spectre and Meltdown chip vulnerabilities, urging HIPAA-covered entities to mitigate the vulnerabilities as part of their risk management processes. The failure to address the computer chip flaws could place the confidentiality, integrity, and availability of protected health information at risk.

HIPAA-covered entities have been advised to read the latest updates on the Spectre and Meltdown chip vulnerabilities issued by the Healthcare Cybersecurity and Communications Integration Center (HCCIC).

What are Spectre and Meltdown?

Spectre and Meltdown are computer chip vulnerabilities present in virtually all computer processors manufactured in the past 10 years. The vulnerabilities could potentially be exploited by malicious actors to bypass data access protections and obtain sensitive data, including passwords and protected health information.

Meltdown is an attack that exploits a hardware vulnerability (CVE-2017-5754) by tricking the CPU into speculatively loading data marked as unreadable or “privileged,” allowing side-channel exfiltration. Spectre is an attack involving two vulnerabilities (CVE-2017- 5753, CVE-2017-5715) in the speculative execution features of CPUs. The first vulnerability is exploited to trick the CPU into mispredicting a branch of code of the attacker’s choosing, with the second used to trick the CPU into speculatively loading the memory allocated to another application on the system. The Meltdown and Spectre chip vulnerabilities can be exploited to gain access to sensitive data, including passwords, cryptographic keys used to protect PII, PHI, or PCI information handled by an application’s database.

Meltdown and Spectre affect computers running on Windows, Mac, Linux and other operating systems. Eradicating the vulnerabilities means replacing chips on all vulnerable devices; however, operating system vendors have been developing patches that will prevent the vulnerabilities from being exploited. Updates have also been made to web browsers to prevent web-based exploitation of the vulnerabilities.

Following the disclosure of the vulnerabilities, HCCIC alerted healthcare organizations about the risk of attack, with the vulnerabilities categorized as a medium threat since local access is generally required to exploit the flaws. However, potentially the flaws can be exploited remotely if users visit a specially crafted website. Browsers are susceptible due to improper checks on JavaScript code, which could lead to information disclosure of browser data.

Mitigating the Threat of Spectre and Meltdown Attacks

Patching operating systems and browsers will mitigate the vulnerabilities, but there may be a cost. The patches can affect system performance, slowing computers by 5-30%. Such a reduction would be noticeable when running high demand computer applications.

There have also been several compatibility issues with anti-virus software and other programs. It is therefore essential for patches to be thoroughly tested before implementation, especially on high value assets and systems containing PII and PHI.

Due to the compatibility issues, Microsoft is only releasing updates for computers that are running anti-virus software that has been confirmed as compatible with the patch. If anti-virus software is not updated, computers will remain vulnerable as the update will not take place. Most anti-virus software companies have now updated their programs, but not all. Kevin Beaumont is maintaining a list of the patch status of AV software.

Web browsers must also be updated to the latest versions. Microsoft has updated Internet Explorer 11 and Microsoft Edge, and Firefox (57.0.4) and Safari (11.0.2) include the update. Google Chrome has also been patched. Healthcare organizations should ensure they are running the latest versions of browsers on all devices to prevent data leakage and operating systems should be patches as soon as possible. One of the main challenges for healthcare organizations is identifying all vulnerable devices – including computers, medical devices and accessory medical equipment – and ensuring they are fully patched.

The vulnerabilities also affect cloud service providers, as their servers also contain computer chips. There could be leakage of PII and PHI from cloud environments if patches have not been applied.

Amazon AWS and Azure have already been patched to protect against Meltdown and Spectre. Healthcare organizations using other managed cloud service providers or private cloud instances should check that they have been patched and are protected against Meltdown and Spectre.

The post HIPAA Covered Entities Urged to Address Spectre and Meltdown Chip Vulnerabilities appeared first on HIPAA Journal.
Summary of Healthcare Data Breaches in December 2017

There was a sharp rise in healthcare data breaches in December, reversing a two-month downward trend. There were 38 healthcare data breaches in December 2017 that impacted more than 500 individuals: An increase of 81% from last month.


December 2017 Healthcare Data Breaches


Unsurprisingly given the sharp increase in reported breaches, the number of records exposed in December also increased month over month. The records of 341,621 individuals were exposed or stolen in December: An increase of 219% from last month.


Records Exposed in December 2017 Healthcare Data Breaches


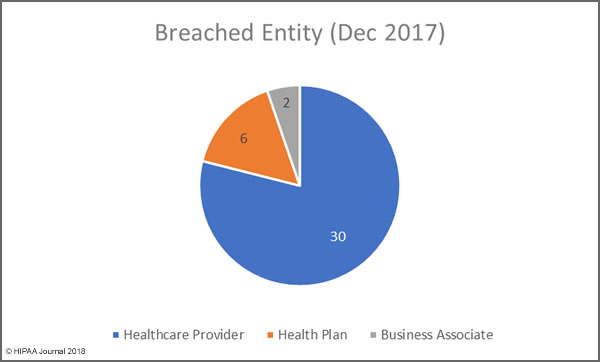
December saw a similar pattern of breaches to past months, with healthcare providers experiencing the most data breaches; however, there was a notable increase in breaches reported by health plans in December – rising from 2 in November to six in December.


December 2017 Healthcare Data Breaches by Covered Entity Type

Causes of Healthcare Data Breaches in December 2017

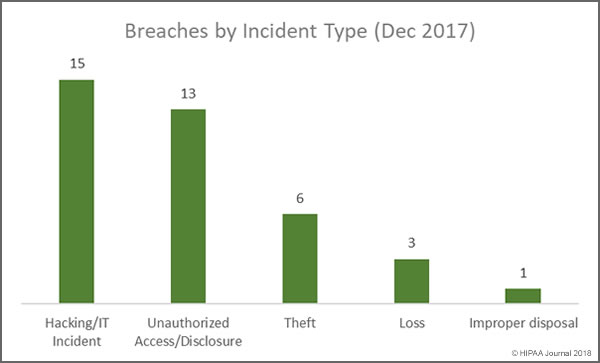
As was the case last month, hacking/IT incidents and unauthorized access/disclosures were the most common causes of healthcare data breaches in December, although there was a notable increase in theft/loss incidents involving portable electronic devices and paper records.


December 2017 healthcare data breaches by incident type


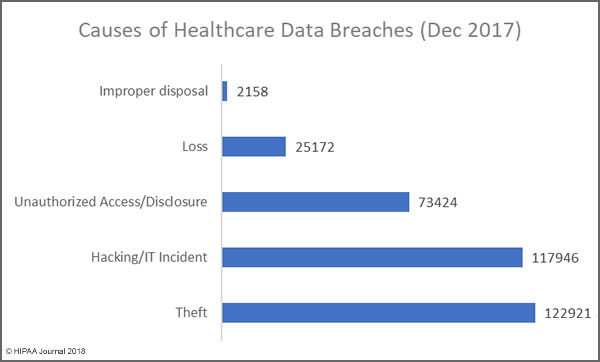
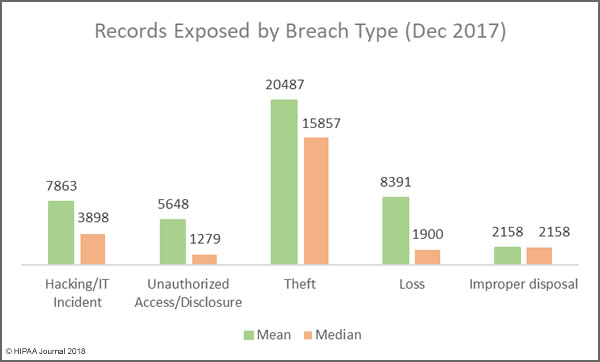
While hacking incidents usually result in the greatest number of records being exposed/stolen, this month saw a major increase in records exposed due to the theft of portable electronic devices. The theft of devices containing PHI – and paper records – resulted in 122,921 patients’ protected health information being exposed. The mean number of records exposed in theft incidents was 20,487 and the median was 15,857 – Both higher than any other cause of data breach.


Causes of Healthcare Data Breaches (Dec 2017)


Records Exposed by Breach Type (Dec 2017)


Network server incidents were the most numerous in December with 12 incidents, although there were 9 incidents involving paper records, showing that while healthcare organizations must ensure appropriate technological defenses are in place to protect electronic data, physical security is also essential to ensure paper records are secured.


Location of Breached PHI (Dec 2017)


10 Largest Healthcare Data Breaches in December 2017

In December, there were 9 data breaches that impacted more than 10,000 individuals reported to the Office for Civil Rights by HIPAA covered entities. In contrast to past months when hacking incidents dominated the top ten breach list, there was an even spread between hacking incidents, unauthorized access/disclosures, and theft of healthcare records and electronic devices.

The largest data breach reported in December affected Oklahoma Department of Human Services. However, this was not a recent data breach. The breach occurred in April 2016, but a breach report was not submitted to the Office for Civil Rights at the time of discovery. It took 18 months after the 60-day deadline for the breach to be reported.

Name of Covered Entity Covered Entity Type Individuals Affected Type of Breach
Oklahoma Department of Human Services Health Plan 47000 Hacking/IT Incident
Henry Ford Health System Healthcare Provider 43563 Theft
Coplin Health Systems Healthcare Provider 43000 Theft
SSM Health Healthcare Provider 29579 Unauthorized Access/Disclosure
UNC Health Care System Healthcare Provider 27113 Theft
Emory Healthcare Healthcare Provider 24000 Unauthorized Access/Disclosure
Franciscan Physician Network of Illinois and Specialty Physicians of Illinois Healthcare Provider 22000 Loss
Longs Peak Family Practice, P.C. Healthcare Provider 16238 Hacking/IT Incident
Sinai Health System Healthcare Provider 11347 Hacking/IT Incident
Golden Rule Insurance Company Health Plan 9305 Unauthorized Access/Disclosure

December 2017 Healthcare Data Breaches by State

California experienced the most healthcare data breaches in December with 5 reported incidents, followed by Michigan with 4 data breaches.

Eight states experienced two data breaches each – Florida, Illinois, Minnesota, New England, Nevada, New York, Philadelphia and Texas.

13 states each had one reported breach: Colorado, Georgia, Iowa, Indiana, Massachusetts, Missouri, New Jersey, North Carolina, Ohio, Oklahoma, Oregon, Tennessee, and West Virginia.

Data source: Department of Health and Human Services’ Office for Civil Rights.

The post Summary of Healthcare Data Breaches in December 2017 appeared first on HIPAA Journal.
Aetna Settles Class Action Lawsuit Filed by Victims of HIV Status Data Breach

Aetna has agreed to settle a class action lawsuit filed by victims of a mailing error that resulted in details of HIV medications prescribed to patients being visible through the clear plastic windows of the envelopes. Aetna was not directly responsible for the mailing, instead an error was made by a third-party vendor.

For some of the patients, the letters had slipped inside the envelope revealing the patient had been prescribed HIV drugs. In many cases, those envelopes were viewed by flat mates, family members, neighbors, friends, and other individuals, thus disclosing each patient’s HIV information. Is not known how many patients had their HIV information disclosed, although the mailing was sent to 13,487 individuals. Some of the patients were being prescribed medications to treat HIV, others were taking the medication as Pre-exposure Prophylaxis (PrEP) to prevent contracting the disease.

Many of the patients who were outed as a result of the breach have faced considerable hardship and discrimination. Several patients have had to seek alternative accommodation after been forced to leave their homes by flat mates and relatives. Others have had personal and family relationships severely damaged as a result of the disclosure.

The Legal Action Center, AIDS Law Project of Pennsylvania, and Berger & Montague, P.C., filed a lawsuit in August seeking damages for the victims of the breach. That lawsuit has been settled for $17,161,200 by Aetna, pending Court approval, with no admission of liability. The settlement also requires Aetna to update its policies and procedures to ensure similar privacy breaches are prevented in the future.

There were two alleged breaches of privacy. There was an improper disclosure of protected health information to Aetna’s legal counsel in July, in addition to the mailing of the Benefit Notices that revealed patients were taking HIV medications. Those privacy breaches violated the Health Insurance Portability and Accountability Act (HIPAA) and several state laws according to the lawsuit.

Individuals who had their PHI improperly disclosed will receive a base payment of $75, while class members who were sent the envelopes with the clear plastic windows will receive a base payment of $500. There are almost 1,600 individuals who will receive the $75 payment and almost 12,000 who will receive a payment of $500.

A fund has also been set up for individuals who have suffered additional harm or losses as a result of the disclosure. Those individuals can apply for additional funds by completing a claim form documenting the financial and non-financial harm they have suffered as a result of the privacy breach.

“Through our outreach efforts, immediate relief program, and this settlement we have worked to address the potential impact to members following this unfortunate incident,” said a spokesperson for Aetna. “In addition, we are implementing measures designed to ensure something like this does not happen again as part of our commitment to best practices in protecting sensitive health information.”

The post Aetna Settles Class Action Lawsuit Filed by Victims of HIV Status Data Breach appeared first on HIPAA Journal.
67% of CISOs Expect a Cyberattack or Data Breach in 2018

The perceived risk of a cyberattack or data breach occurring has increased year on year, according to a new survey conducted by the Ponemon Institute.

The Opus-sponsored survey was conducted on 612 CISOs, CIOs, and other information security professionals, who were asked questions about data security and cyber risk.

The survey revealed confidence in cybersecurity defenses is getting worse, with more than 67% of respondents now believing they will experience a data breach or cyberattack in 2018. Last year, 60% of respondents thought they would likely experience a data breach or cyberattack in 2017.

Hackers have been responsible for a large number of data breaches over the past 12 months and the threat from malware is greater than ever, but the biggest perceived data security risk comes from within. 70% of respondents said the most probable cause of a data breach was a lack of competent in-house staff, with 64% of respondents saying a lack of in-house expertise would likely result in a data breach.

Cyberattacks and malware infections are likely causes of data breaches, but the biggest threat is phishing. Respondents to the survey believed there was a 65% chance of their organization experiencing credential theft as a result of a careless employee falling for phishing scams. Malware infections were expected by 61% of respondents, while cyberattacks resulting in significant downtime were expected by 59% of respondents.

Other probable causes of data breaches were the inability to protect sensitive data (59% of respondents), the inability to keep up with increasingly sophisticated cyberattacks (56% of respondents), and the inability to control the use of sensitive data by third parties (51% of respondents).

The increased use of Internet of Things (IoT) devices is a major risk. 60% of respondents rated IoT devices as the most difficult to secure, followed by mobile devices (54%) and cloud services (50%).

The rapidly changing threat landscape and the broadening of the attack surface means defending an organization from cyberattacks has increased significantly, and as a result, jobs in information security have become harder.

69% of respondents believe their jobs will become more stressful in 2018, while there is also fear that if a data breach is experienced, heads will roll. 45% of respondents were worried they would lose their jobs following a cyberattack on their organization.

Previous surveys have shown a lack of board involvement in cybersecurity, although that does appear to be changing. Half of respondents said the C-Suite was becoming more involved in cybersecurity matters, while a third of respondents said the path to an improved security posture is clear.

Perhaps unsurprisingly considering how employees are perceived to be the main threat, top areas for improvement were staffing, better leadership, and more actionable cyber-intelligence. Technology improvements were also deemed a necessity. However, even though the risk of a cyberattack is increasing, IT security budgets are not. Information security professionals must therefore make budgets go further.

“Once again, we find that people – not just third parties – are the weak link in information security. Smart companies can’t prevent all data breaches, but implementing solid risk management programs supported by good governance, training, proven frameworks and robust technology will go a long way to reducing risk and alleviating CISO stress,” said Dov Goldman, VP, Innovation & Alliances of Opus.

Data breaches and cyber-attacks continue to plague organizations and the responsibility of protecting sensitive data stops with the CISO. It’s critical that companies support CISOs and reduce risk by implementing standard processes, including policy review and documentation, senior leadership and board member oversight, as well as other safeguards to reduce their vulnerability,” said Dr. Larry Ponemon, Chairman and Founder of the Ponemon Institute.

The post 67% of CISOs Expect a Cyberattack or Data Breach in 2018 appeared first on HIPAA Journal.
1,300 Patients’ Medical Records Viewed Without Authorization by Palomar Health Nurse

More than 1,300 patients of Palomar Medical Center Escondido are being notified that a former nurse viewed their medical records without authorization while they were receiving treatment at the hospital.

The privacy violations occurred over a 15-month period between February 10, 2016 and May 7, 2017. The unauthorized access was discovered when access logs were reviewed. The audit revealed a pattern of access that was not consistent with the nurse’s work duties.

The audit showed the nurse had viewed the records of patients that had been assigned to her, in addition to patients assigned to another nurse in the same unit.

The incident appears to be a case of snooping, rather than data access with malicious intent. Palomar Health has uncovered no evidence to suggest any information was recorded and removed from the hospital, and no reports have been received to suggest any patient information has been misused. Following an internal investigation into the privacy violations, the nurse resigned.

The information viewed was limited to names, dates of birth, genders, medical record numbers, treatment locations, diagnoses, allergies, and medications for 1,309 patients. Financial information, insurance details, and Social Security numbers of four patients were present in a part of the medical record system that was accessed by the nurse. Those four patients have been offered identity theft protection services.

Palomar Health is currently implementing a new system that will automatically audit the logs created when medical records are viewed and when access attempts are made. The system will allow the health system to rapidly identify cases of snooping and data theft. Staff at the hospital will also receive additional privacy and security awareness training.

The post 1,300 Patients’ Medical Records Viewed Without Authorization by Palomar Health Nurse appeared first on HIPAA Journal.
Patients in Connecticut Can Now Sue Healthcare Providers for Privacy Violations

There is no private cause of action in the Health Insurance Portability and Accountability Act, so patients are not permitted to sue healthcare providers for privacy violations.

However, there have been rulings in several states, including New York, Missouri, and Massachusetts, allowing patients to file lawsuits against healthcare providers over unauthorized and negligent disclosures of medical records.

Following a ruling by the Connecticut Supreme Court last week, Connecticut residents will be permitted to file lawsuits for damages following negligent disclosures of medical records that have resulted in harm.

The legal precedent was set by the Supreme Court in the case Byrne v. Avery Center for Obstetrics & Gynecology.

Emily Byrne filed a lawsuit against Avery Center for Obstetrics and Gynecology (ACOG) after her medical records were disclosed to a man seeking custody of her child in a paternity suit.

ACOG was issued with a subpoena to appear before an attorney and supply Byrne’s medical records. ACOG did not challenge the subpoena, made no attempt to limit disclosure, and simply mailed a copy of Byrne’s medical file to the New Haven Regional Children’s Probate Court, where the records were made available to the man seeking custody of her child.

Byrne and her attorney, Bruce L. Elstein of Trumbull, claimed this amounted to negligence and breach of contract. ACOG claimed that under HIPAA Rules, patient consent was not required before medical records were disclosed in response to a subpoena.

Byrne argued that HIPAA creates a standard of care for patient medical records, and Avery violated that standard by releasing her records. Byrne lost the case in the Superior Court, which ruled that HIPAA does not permit private suits to be filed against healthcare providers for HIPAA violations. Byrne appealed, and the case was heard by the Supreme Court, which ruled in 2014 that HIPAA could be used as a standard of care for common law claims.

The case went before the Supreme Court for a second time after the trial court deferred the case as no courts had addressed the issue of negligence.  The Supreme Court disagreed with ACOG’s argument that patient consent is not required before medical records are disclosed in response to a subpoena, saying federal laws require the provider to have “satisfactory assurances” that a patient has been given notice about the request.

In this case, satisfactory assurances had not been obtained. Justice Dennis G. Eveleigh wrote, “the defendant did not even comply with the face of the subpoena.”

In the ruling, Justice Eveleigh wrote, “The dispositive issue in this appeal is whether a patient has a civil remedy against a physician if that physician, without the patient’s consent, discloses confidential information obtained in the course of the physician-patient relationship.’’

“We agree with the majority of jurisdictions that have considered the issue, and conclude that the nature of the physician-patient relationship warrants recognition of a common-law cause of action for breach of the duty of confidentiality in the context of that relationship.”

“Finally, we have a remedy in Connecticut that recognizes that there is a duty of confidentiality, the breach of which can lead to compensation for damages,” said Elstein.

The post Patients in Connecticut Can Now Sue Healthcare Providers for Privacy Violations appeared first on HIPAA Journal.
HIPAA Retention Requirements

The reason the HIPAA retention requirements need clarifying is that the distinction between HIPAA medical records retention and HIPAA record retention can be confusing.

This article aims to clarify what records should be retained under HIPAA compliance rules, and what other data retention requirements Covered Entities and Business Associates may have to consider.

Throughout the Administrative Simplification Regulations of HIPAA, there are several references to HIPAA data retention. These generally fall into two categories – HIPAA medical records retention and HIPAA records retention requirements. The distinction between the two categories is that there are no HIPAA medical records retention requirements, but requirements exist for other documentation.

Read about email retention requirements in our recent HIPAA compliant email retention solution review

One of the reasons the lack of HIPAA medical records retention requirements can be confusing is that, under the Privacy Rule, individuals can request access to and amendment of Protected Health Information “for as long as Protected Health Information is maintained in a designated record set”. However, Covered Entities and Business Associates are required to provide an accounting of disclosures of Protected Health Information for the six years prior to a request.

Why There is No HIPAA Medical Records Retention Period

The reason the Privacy Rule does not stipulate how long medical records should be retained is that there is no mandated HIPAA medical records retention period. This is because each state has its own laws governing the retention of medical records, and – unlike in other areas of the Healthcare Insurance Portability and Accountability Act – HIPAA does not pre-empt state data retention laws.

Consequently, each Covered Entity and Business Associate is bound by state law with regard to how long medical records have to be retained rather than any specific HIPAA medical records retention period. States’ retention periods can vary considerably depending on the nature of the records and to whom they belong. For example:

  • In Arkansas, adults´ hospital medical records must be retained for ten years after discharge but master patient index data must be retained permanently.
  • In Florida, physicians must maintain medical records for five years after the last patient contact, whereas hospitals must maintain them for seven years.
  • In Georgia, doctors have to retain any evaluation, diagnosis, prognosis, laboratory report, or biopsy slide in a patient’s record for ten years from the date it was created.
  • In Nevada, healthcare providers are required to maintain medical records for a minimum of five years, or – in the case of a minor – until the patient has reached twenty-three years of age.
  • In North Carolina, hospitals must maintain patients’ records for eleven years from the date of discharge, and records relating to minors must be retained until the patient has reached thirty years of age.

What HIPAA Retention Requirements Exist for Other Documentation?

Although there are no HIPAA retention requirements for medical records, there are requirements for how long other HIPAA-related documents should be retained. These requirements are covered in 45 CFR 164.316 and 45 CFR 164.530 – both of which state Covered Entities and Business Associates must document policies and procedures implemented to comply [with HIPAA] and records of any action, activity, or assessment with regards to the policies and procedures, or sufficient to meet the burden of proof under the Breach Notification Rule.

Both standards also stipulate documents must be retained for a minimum of six years from when the document was created, or – in the event of a policy – from when it was last in effect. Therefore, if a policy is implemented for three years before being revised, a record of the original policy must be retained for a minimum of nine years after its creation. These HIPAA data retention requirements preempt state laws if they require shorter periods of document retention.

The list of documents subject to the HIPAA retention requirements depends on the nature of the business conducted by the Covered Entity or Business Associate. The following list is an example of the most common types of documents subject to the HIPAA document retention requirements; but, for example, healthcare clearinghouses do not issue Notices of Privacy Practices, so would not be required to retain copies of them:

  • Notices of Privacy Practices.
  • Authorizations for Disclosures of PHI.
  • Risk Assessments and Risk Analyses.
  • Disaster Recovery and Contingency Plans.
  • Business Associate Agreements.
  • Information Security and Privacy Policies.
  • Employee Sanction Policies.
  • Incident and Breach Notification Documentation.
  • Complaint and Resolution Documentation.
  • Physical Security Maintenance Records.
  • Logs Recording Access to and Updating of PHI.
  • IT Security System Reviews (including new procedures or technologies implemented).

What Else to Consider in Addition to HIPAA Record Retention

It was mentioned above the HIPAA retention requirements can be confusing; and when some other regulatory requirements are taken into account, this may certainly be the case. This is because – for example – in addition to HIPAA records retention, health insurance companies may be subject to the complexities of FINRA, while employers that are Covered Entities may have to comply with the record retention requirements of the Employee Retirement Income Security Act and Fair Labor Standards Act. In some cases, this can mean retaining records indefinitely.

The Centers for Medicare & Medicaid Services (CMS) requires records of healthcare providers submitting cost reports to be retained for a period of at least five years after the closure of the cost report, and that Medicare managed care program providers retain their records for ten years. Providers and suppliers need to maintain medical records for each Medicare beneficiary that is their patient. Although much of the documentation supporting CMS cost reports will be the same as those required for HIPAA record retention purposes, the two sets of records must be kept separate for retrieval purposes.

For all Covered Entities and Business Associates, it is recommended any documentation that may be required in a personal injury or breach of contract dispute is retained for as long as necessary. “As long as necessary” will depend on the relevant Statute of Limitations in force in the state in which the entity operates. In many cases, Statutes of Limitation are longer than any HIPAA record retention periods.

HIPAA Record Retention and Destruction/Disposal

When the required retention periods for medical records and HIPAA documentation have been reached, HIPAA requires all forms of PHI to be destructed or disposed of securely to prevent impermissible disclosures of PHI. The Privacy and Security Rules do not require a particular disposal method and the HHS recommends Covered Entities and Business Associates review their circumstances to determine what steps are reasonable to safeguard PHI through destruction and disposal.

HHS also suggests some secure methods for destructing or disposing of PHI once the HIPAA data retention requirements have expired. With regards to paper records, the agency suggests shredding, burning, pulping, or pulverizing the records so that PHI is rendered essentially unreadable, indecipherable, and otherwise cannot be reconstructed, while for other physical PHI such as labeled prescription bottles, HHS suggests using a disposal vendor as a business associate to pick up and shred or otherwise destroy the PHI.

With regards to electronic PHI, HIPAA requires that Business Associates return or destroy all PHI at the termination of a Business Associate Agreement. In order to comply with this standard, HHS suggests clearing (using software or hardware products to overwrite media with non-sensitive data), purging (degaussing or exposing the media to a strong magnetic field in order to disrupt the recorded magnetic domains), or destroying the media (disintegration, pulverization, melting, incinerating, or shredding) – methods that could also be used by a Covered Entity when PHI or documentation is no longer subject to the HIPAA retention requirements.

HIPAA Retention Requirements – FAQS

How long does a covered entity have to retain a patient authorization for the disclosure of PHI?

A Covered Entity has to retain patient authorization for the disclosure of PHI for six years. However, if the document is part of the patient´s medical record, it is subject to the state´s medical record retention requirements – which could be longer. Furthermore, if the covered entity operates in a state in which the Statute of Limitations for private rights of action exceeds six years, it will be necessary to retain the document until the Statute of Limitations has expired.

Why are IT security system reviews considered HIPAA-related documents?

IT security system reviews are considered HIPAA-related documents because under the technical safeguards of the HIPAA Security Rule, covered entities are required to enforce IT security measures such as access controls, password policies, automatic log-off, and audit controls regardless of whether systems are being used to access ePHI. These measures would ordinarily be included in an IT security system review, and therefore the reviews have to be retained for a minimum of six years.

How should covered entities and business associates dispose of HIPAA-related documentation?

Covered entities and business associates should dispose of HIPAA-related documentation in the same way as HHS recommends disposing of PHI. For paper records, this means “shredding, burning, pulping, or pulverizing the records so that PHI is rendered essentially unreadable, indecipherable, and otherwise cannot be reconstructed”. For ePHI and documentation maintained on electronic media, HHS recommends clearing or purging the data, or destroying the media by pulverization, melting, or incinerating.

Can covered entities and business associates be fined for the improper disposal of HIPAA-related documentation?

There have been no cases of a covered entity or business associate being fined for the improper disposal of HIPAA-related documentation, there have been multiple penalties issued by HHS for the improper disposal of PHI. Therefore, in case a document contains both HIPAA-related documentation and PHI (for example, a patient authorization) it is in the organizations’ best interests to train staff on the correct manner to dispose of all documentation relating to healthcare activities.

What are the Administrative Simplification Regulations of HIPAA?

The Administrative Simplification Regulations of HIPAA contain the Rules and standards developed by the Department of Health & Human Services (HHS) to comply with Title II of HIPAA and Subtitle D of the HITECH Act. The Administrative Simplification Regulations not only include the Privacy, Security, and Breach Notification Rules, but also the General Administrative Requirements, the standards for covered transactions, and the Enforcement Rule – which describes how HHS conducts compliance investigations.

When does HIPAA pre-empt state data retention laws?

HIPAA pre-empts state data retention laws when a state has a law requiring the retention of policy documents for (say) five years, but some of those documents are subject to the HIPAA data retention requirements (i.e., complaint and resolution documentation). In such cases, the documents subject to HIPAA data retention requirements must be retained for a minimum of six years rather than five.

If HIPAA states PHI has to be retained for six years, but a state law requires medical records to be retained for ten years, which law takes precedence?

If HIPAA states PHI has to be retained for six years, but a state law requires medical records to be retained for ten years neither law takes precedence over the other because the two laws are relating to different types of information.

The HIPAA data retention requirements only apply to documentation such as policies, procedures, assessments, and reviews. Therefore, Covered Entities should comply with the relevant state law for medical record retention.

However, when the medical record retention period has expired, and medical records are destroyed, HIPAA stipulates how they should be destroyed to prevent impermissible disclosures of PHI. The same processes should also be used for the destruction of HIPAA documentation.

What is the burden of proof under the Breach Notification Rule?

The burden of proof under the Breach Notification Rule relates to impermissible uses or disclosures of unsecured PHI which may qualify as a data breach. Under the Breach Notification Rule, Covered Entities and Business Associates have the burden of proof to demonstrate that an impermissible use or disclosure of unsecured PHI did not constitute a data breach if not notifying it to affected individuals and HHS’ Office for Civil Rights.

If such an event does constitute a notifiable data breach, Covered Entities, and Business Associates also have the burden of proof to demonstrate that all required notifications have been made (i.e., to the individual, to HHS´ Office for Civil Rights, and – when necessary – to the media).

How long is it necessary to retain authorizations for disclosures of PHI?

Authorizations for disclosures of PHI not permitted by the Privacy Rule should include an expiration date or an expiration event that relates to the individual or the purpose of the disclosure (i.e., “end of research study”). The six-year HIPAA retention period finishes six years after the expiration date or event rather than six years after the authorization is signed.

What is the difference between HIPAA record retention and HIPAA data retention?

The difference between HIPAA record retention and HIPAA data is that the term HIPAA record retention is most commonly associated with HIPAA documentation (risk assessments, policies, security reviews, patient access requests, etc.), while the term HIPAA data retention most often relates to PHI – for which there are no HIPAA retention requirements. The retention requirements for PHI are individually mandated by each state.

Are there any HIPAA medical record retention requirements?

There are no HIPAA medical record retention requirements because each state sets its own retention requirements for medical records. State-by-state requirements can be found in this PDF. However, when medical records reach the end of the retention period, the medical records have to be disposed of – or destructed – in compliance with HIPAA.

For medical records stored on paper, this means “shredding, burning, pulping, or pulverizing the records so that PHI is rendered essentially unreadable, indecipherable, and otherwise cannot be reconstructed”. For medical records stored electronically, HHS recommends clearing or purging the data, or destroying media by pulverization, melting, or incinerating.

Why do some articles assert HIPAA data retention is 7 years, rather than 6 years?

Some articles assert HIPAA data retention is 7 years, rather than 6 years, when they confuse the HIPAA retention requirements with the medical record requirements mandated by a particular state. For example, California, Indiana, and Pennsylvania are among a number of states that require doctors and/or hospitals to retain medical records for a minimum of 7 years.

The HIPAA retention requirements are always 6 years after a HIPAA-related document is last in force. This means that if a policy is created to comply with HIPAA in 2010, and is in force until 2020 (when it is replaced with a new policy), the original policy document has to be retained for 16 years – the ten years it was in force and the six years following.

What are the CMS record retention requirements of 10 years?

The CMS record retention requirements of 10 years apply to Medicare managed care program providers – such as providers of Medicare Advantage plans. Program providers, rather than healthcare organizations that provide services for program participants, have to maintain patient records for a minimum of ten years unless longer state retention requirements exist.

What are the PHI retention requirements under HIPAA?

There are no PHI retention requirements under HIPAA because PHI is maintained in “designated record sets” of payment and medical records, and each state sets its own medical record retention period. However, when the state-mandated medical record retention period comes to an end, PHI must be destroyed or disposed of in compliance with HIPAA.

What are the HIPAA log retention requirements?

The HIPAA log retention requirements are that if a log, note, or record relates to a HIPAA policy or procedure, the log, note, or record must be retained for six years from the date the content was last used or was last effective.

For example, the Security Rule requires Covered Entities and Business Associates to regularly review records of information system activity. A review of this nature would involve analyzing access reports and audit logs. As the access reports and audit logs are key to any new procedures implemented as a result of the review, they must be retained for at least six years from the date of the next review when they will be replaced with more up-to-date access reports and audit logs.

Where can I find a HIPAA data retention policy template?

There is no such thing as a HIPAA data retention policy template because there is no such thing as “HIPAA data”. The term is often mistakenly used to refer to PHI because the Privacy Rule protects PHI. However, each state applies its own data retention requirements for medical records, so medical data retention policies should comply with state laws rather than HIPAA.

What are the HIPAA backup retention requirements?

There are no HIPAA backup retention requirements inasmuch as HIPAA does not dictate how long backups should be retained. However, if data is being backed before being permanently removed from a system (for example, to free up storage space), and the data contains HIPAA-related documentation, the backup will have to be retained for six years after the HIPAA-related documentation was last used or was last effective.

In this scenario, it is important that the backup media is protected by the physical safeguards of the Security Rule to prevent unauthorized access. It is also important to note that some backup media have limits on how long they are able to retain data. For example, data maintained on USB drives can deteriorate within five years – making them unsuitable for saving HIPAA documentation as it will not be possible to recover the documentation when required.

The post HIPAA Retention Requirements appeared first on HIPAA Journal.